

What causes onion-skin periosteal reaction in bone on radiographic imaging?
Let me know in the comments.
Click to reveal the answer
Answer:
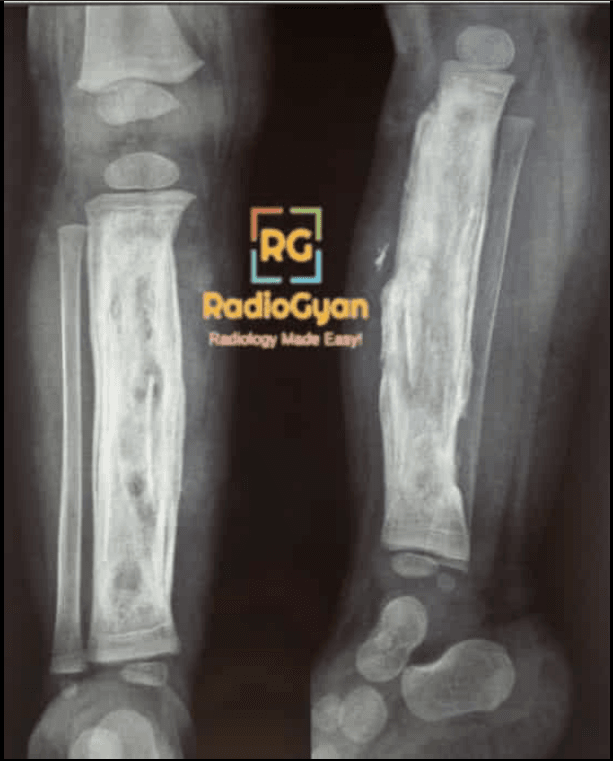
Onion skin appearance on a radiograph is lamellated periosteal reaction:
several concentric layers of new bone laid down parallel to the cortex. It signals a lesion growing at
roughly the limit of the bone’s ability to wall it off, so it is an intermediate-aggressiveness pattern
rather than proof of malignancy [1,2].

Why is it called so?
The concentric layers of new bone resemble the rings of a cut onion. The alternative names,
lamellated and multilayered, describe the same thing without the metaphor.
Pathophysiology
The periosteum has an outer fibrous layer and an inner cambial layer that is osteogenic [2]. When a
lesion expands in bursts, the cambial layer gets just enough time between episodes to lay down a thin
sheet of bone before being lifted again. Each cycle adds one lamella, and the stack is what the
radiograph shows. A process slow enough for the periosteum to keep pace builds one solid shell; one
fast enough to outrun it produces spicules or a Codman triangle [1].
Alternative names: Lamellated periosteal reaction, Multilamellar periosteal reaction,
Laminated periosteal reaction, Onion peel appearance
Other associated named signs:
Codman triangle,
Sunburst periosteal reaction
What onion skin periosteal reaction actually tells you
It tells you about speed, not histology. Single lamellar reactions occur in acute, usually benign
disease, whereas multilamellar reactions carry intermediate aggressiveness and a growth rate close to
the limit of the walling-off capability of the bone [2]. That is why the pattern has so many mimics:
anything sitting at that boundary, tumour or not, produces it. The more useful question is how the
reaction is distributed. Diffuse favours a systemic rheumatological, metabolic or haematological cause;
localised points to a focal lesion [1].
Causes of onion skin periosteal reaction
| Distribution | Cause | What points to it |
|---|---|---|
| One bone, child or adolescent | Ewing sarcoma | Diaphyseal, permeative, soft-tissue mass out of proportion to the bone change |
| One bone, child or adolescent | Osteosarcoma | Metaphyseal, cloud-like matrix, usually spiculated rather than cleanly layered |
| One bone, any age | Acute or subacute osteomyelitis | Fever, raised CRP, cortical lucency, later a sequestrum in an involucrum |
| One bone, age 7 to 12, girls more often | Chronic nonbacterial osteomyelitis (CNO, CRMO) | Metaphyseal pain without sepsis, inflammatory markers normal or mildly raised |
| One bone, under 1 year | Caffey disease (infantile cortical hyperostosis) | Irritable infant, mandible or long-bone diaphysis, exuberant new bone within 2 weeks |
| One bone, child | Langerhans cell histiocytosis | Lytic lesion of skull, spine or femur, variable aggressiveness |
| One bone, athlete or recruit | Stress injury | Focal cortical thickening at a known stress site, load-related pain |
| Many bones, symmetric | Hypertrophic osteoarthropathy | Clubbing, arthralgia, tibia and fibula, an underlying thoracic cause |
| Many bones, symmetric | Thalassaemia and sickle cell disease | Marrow expansion, coarse trabeculae, known haemoglobinopathy |
| Many bones, infant | Congenital syphilis | Symmetric metaphyseal lucency, Wimberger sign, maternal serology |
| Many bones | Hypervitaminosis A, scurvy, venous stasis | Dietary or drug history, chronic limb oedema |
How onion skin differs from the other periosteal reaction patterns
| Pattern | Appearance | Implied behaviour |
|---|---|---|
| Solid, continuous | A single thick, uninterrupted shell fused to the cortex | Slow. The periosteum has kept up and walled the process off [1,2] |
| Single lamella | One thin layer separated from the cortex by a lucent line | Acute, and usually benign [2] |
| Onion skin (lamellated, multilayered) | Several concentric layers parallel to the cortex | Intermediate. Growth close to the limit of the bone’s walling-off capacity [2] |
| Sunburst (spiculated) | Fine spicules radiating perpendicular to the cortex | Fast. The periosteum is outpaced [1] |
| Codman triangle | A cuff of new bone where periosteum is stripped from cortex | Fast, and only the edge of the lesion is ossified [1] |
Is onion skin appearance diagnostic of Ewing sarcoma?
No. Ewing sarcoma is a highly aggressive small round cell sarcoma of children and adolescents, and
radiographs and CT do show its destruction, cortical breach and periosteal reaction, with MRI defining
intramedullary and soft-tissue extent and skip lesions [4]. But the lamellated pattern is neither
sensitive nor specific for it. Monostotic Caffey disease of the femur in an infant produced a lamellated
diaphyseal reaction that masqueraded as a bone tumour; MRI showed muscle oedema with no soft-tissue
proliferation, marrow signal change or cortical breach, and the lesion remodelled by six months [5]. In a
five-year-old, chronic nonbacterial osteomyelitis of the humerus produced a permeative lesion with a
multilayered reaction and cortical breakthrough on MRI; osteosarcoma and Ewing sarcoma were both raised,
and CT-guided biopsy was needed to show chronic inflammation with no neoplasia or infection [6].
How to report it
- Name the pattern and say what it implies: lamellated, intermediate aggressiveness, not a diagnosis.
- State whether it is one bone or many. This is the most useful discriminator [1].
- Give the age, the bone and the segment. Diaphyseal in an adolescent reads very differently from
metaphyseal in an infant. - Say what the periosteum is reacting to: permeative destruction, a soft-tissue mass, cortical lucency
or nothing visible. - If biopsy is planned, say where. Sample the site of the most aggressive pattern, which improves
grading and the detection of tumour cells and bone matrix [1].
Onion skin appearance outside bone
The same metaphor is used for an unrelated finding that shares the search term.
| Where | Modality and appearance | What it means |
|---|---|---|
| Bone (this page) | Radiograph or CT: concentric layers of new bone around the cortex | Lamellated periosteal reaction, intermediate aggressiveness |
| Testis | Ultrasound or MRI: concentric rings in an avascular intratesticular mass | Onion skin sign of a testicular epidermoid cyst, benign, supports testis-sparing surgery [7] |
Frequently asked questions
What does onion skin appearance on X-ray mean?
Onion skin appearance means lamellated periosteal reaction: several concentric layers of new bone parallel to the cortex. It indicates a process growing close to the limit of the bone’s ability to wall it off, so it is an intermediate-aggressiveness pattern, not a specific diagnosis.
Which conditions cause onion skin periosteal reaction?
In one bone: Ewing sarcoma, osteosarcoma, osteomyelitis, chronic nonbacterial osteomyelitis, Langerhans cell histiocytosis, Caffey disease and stress injury. In many bones: hypertrophic osteoarthropathy, thalassaemia, sickle cell disease, congenital syphilis, hypervitaminosis A, scurvy and venous stasis.
Is onion skin periosteal reaction always Ewing sarcoma?
No. Monostotic Caffey disease has produced a lamellated reaction that masqueraded as a bone tumour, and chronic nonbacterial osteomyelitis has produced a multilayered reaction that raised osteosarcoma and Ewing sarcoma until biopsy excluded both. The pattern alone does not make the diagnosis.
What is the difference between onion skin and sunburst periosteal reaction?
Onion skin layers run parallel to the cortex and imply intermediate growth, the periosteum managing a thin layer before being lifted again. Sunburst spicules run perpendicular to the cortex and imply faster growth that has outpaced the periosteum entirely.
References
- Allen H, Barnthouse NC, Chan BY. Periosteal pathologic conditions: imaging findings and pathophysiology. Radiographics. 2023;43(2):e220120. PMID: 36525365.
- Bisseret D, Kaci R, Lafage-Proust MH, Alison M, Parlier-Cuau C, Laredo JD, et al. Periosteum: characteristic imaging findings with emphasis on radiologic-pathologic comparisons. Skeletal Radiol. 2015;44(3):321-38. PMID: 25269751.
- Rana RS, Wu JS, Eisenberg RL. Periosteal reaction. AJR Am J Roentgenol. 2009;193(4):W259-72. PMID: 19770293.
- Matcuk GR, Tivorsak T, Watterson CT, Errani C, Aiba H, Crombe A, et al. Imaging of Ewing sarcoma: an updated analysis including presenting features, prognostic imaging biomarkers, and treatment response assessment. Skeletal Radiol. 2026;55(9):2195-217. PMID: 42062585.
- Kumari M, Prasad SN, Meena A, Tekkali KPK. Monostotic femoral Caffey disease masquerading as Ewing sarcoma. BMJ Case Rep. 2024;17(9):e261790. PMID: 39349301.
- Fahmy AN, Everingham M, Kim C, Kumar A. Chronic nonbacterial osteomyelitis in a young child: a case report of a diagnostic challenge mimicking malignancy. Cureus. 2025;17(6):e85684. PMID: 40642690.
- Langer JE, Ramchandani P, Siegelman ES, Banner MP. Epidermoid cysts of the testicle: sonographic and MR imaging features. AJR Am J Roentgenol. 1999;173(5):1295-9. PMID: 10541108.
Access all radiology signs posted so far: https://radiogyan.com/radiology-signs/
Improve Content And Help Your Colleagues!
Found an error in the post? Please let us know using our contact page and we will update it with due credits!
If you wish to contribute radiological images for this case (or any other article on the website), you can submit them here and you will be duly credited: Submit radiology case