

Bosniak Classification Calculator (Version 2019) for Renal Cysts on CT and MRI
What modality are you using to evalute the renal mass?
Quick References:
Other useful tools
Bosniak Classification of Cystic Renal Masses (Version 2019)
The Bosniak classification stratifies a cystic renal mass into one of five classes (I, II, IIF, III, IV) on the basis of imaging features, and each class carries a different likelihood of malignancy and a different management pathway. It was proposed by Morton Bosniak in 1986 and revised in 1993 and 2005. The current version, Bosniak version 2019 (v2019), was published by Silverman, Davenport and colleagues in Radiology and replaced much of the earlier subjective wording with measurable thresholds.
Three things changed the way the system is used. First, v2019 gives numeric definitions for wall and septal thickness, septal number and protrusion size, so two readers grading the same mass are far more likely to agree. Second, it formally incorporates MRI alongside CT. Third, it deliberately narrows what counts as class IIF and class III, which shifts a large number of masses down into class II and reduces unnecessary surveillance and surgery.
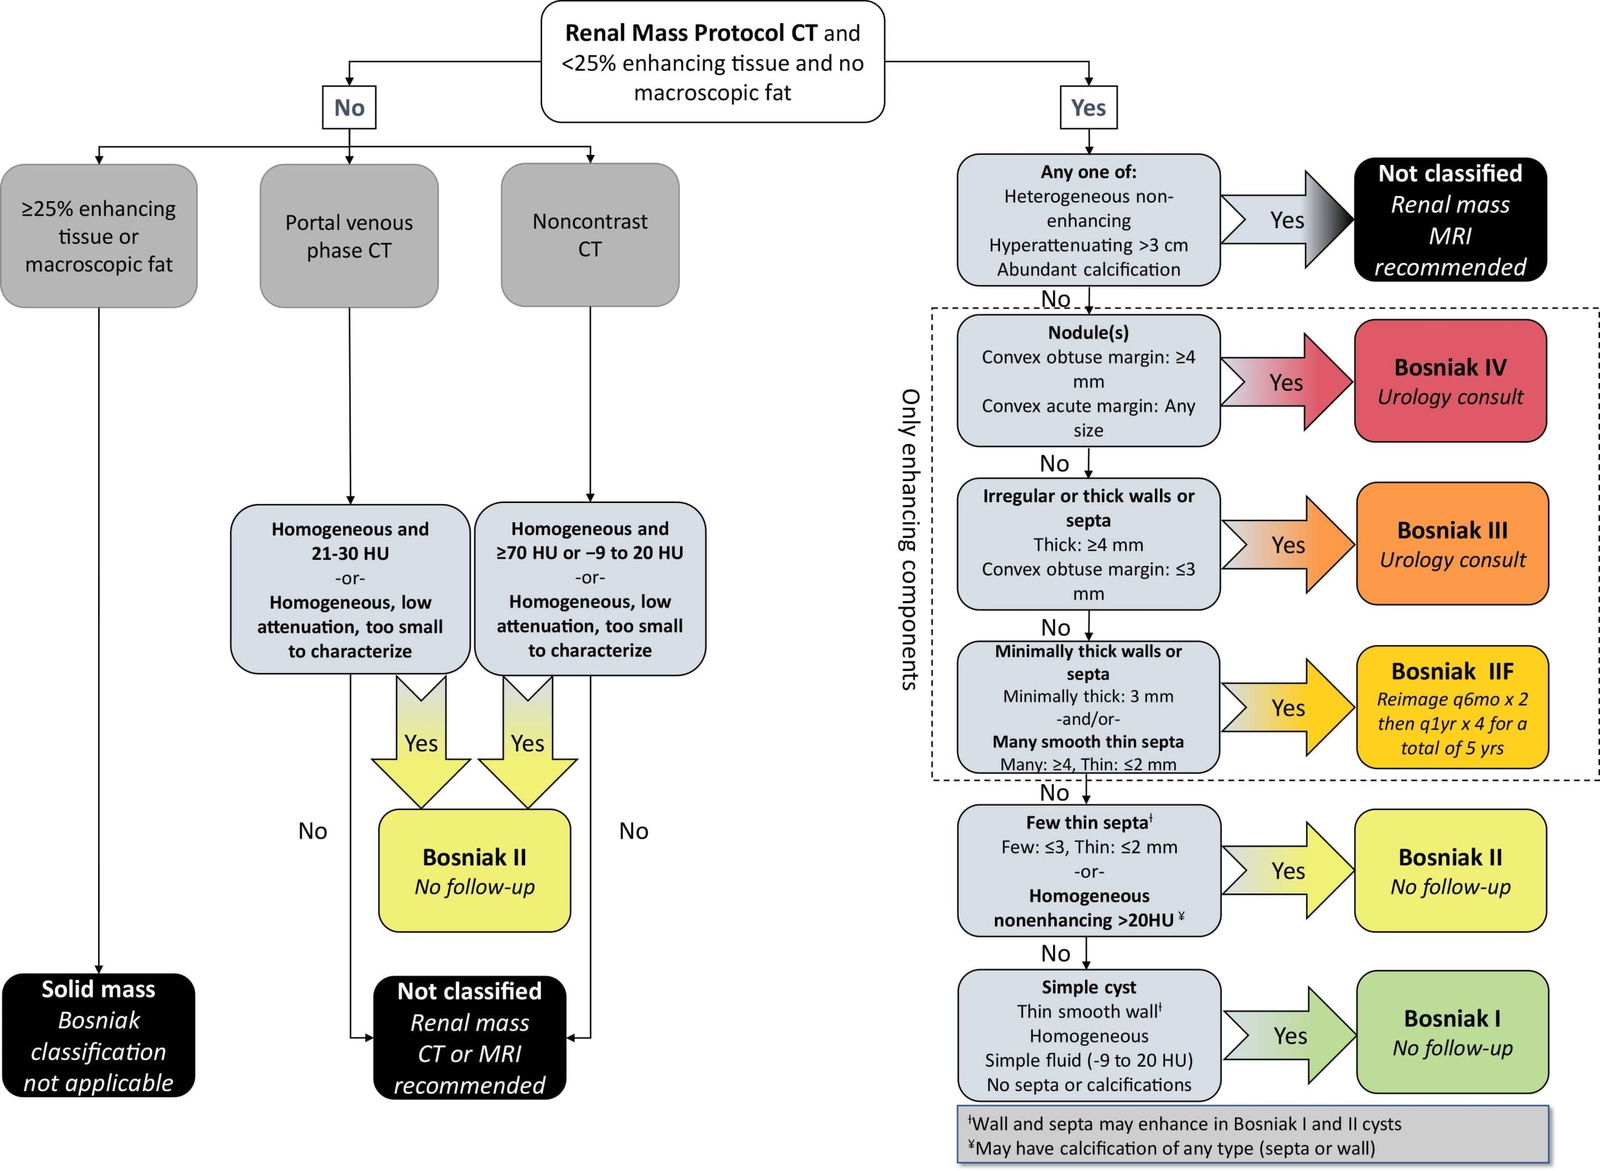
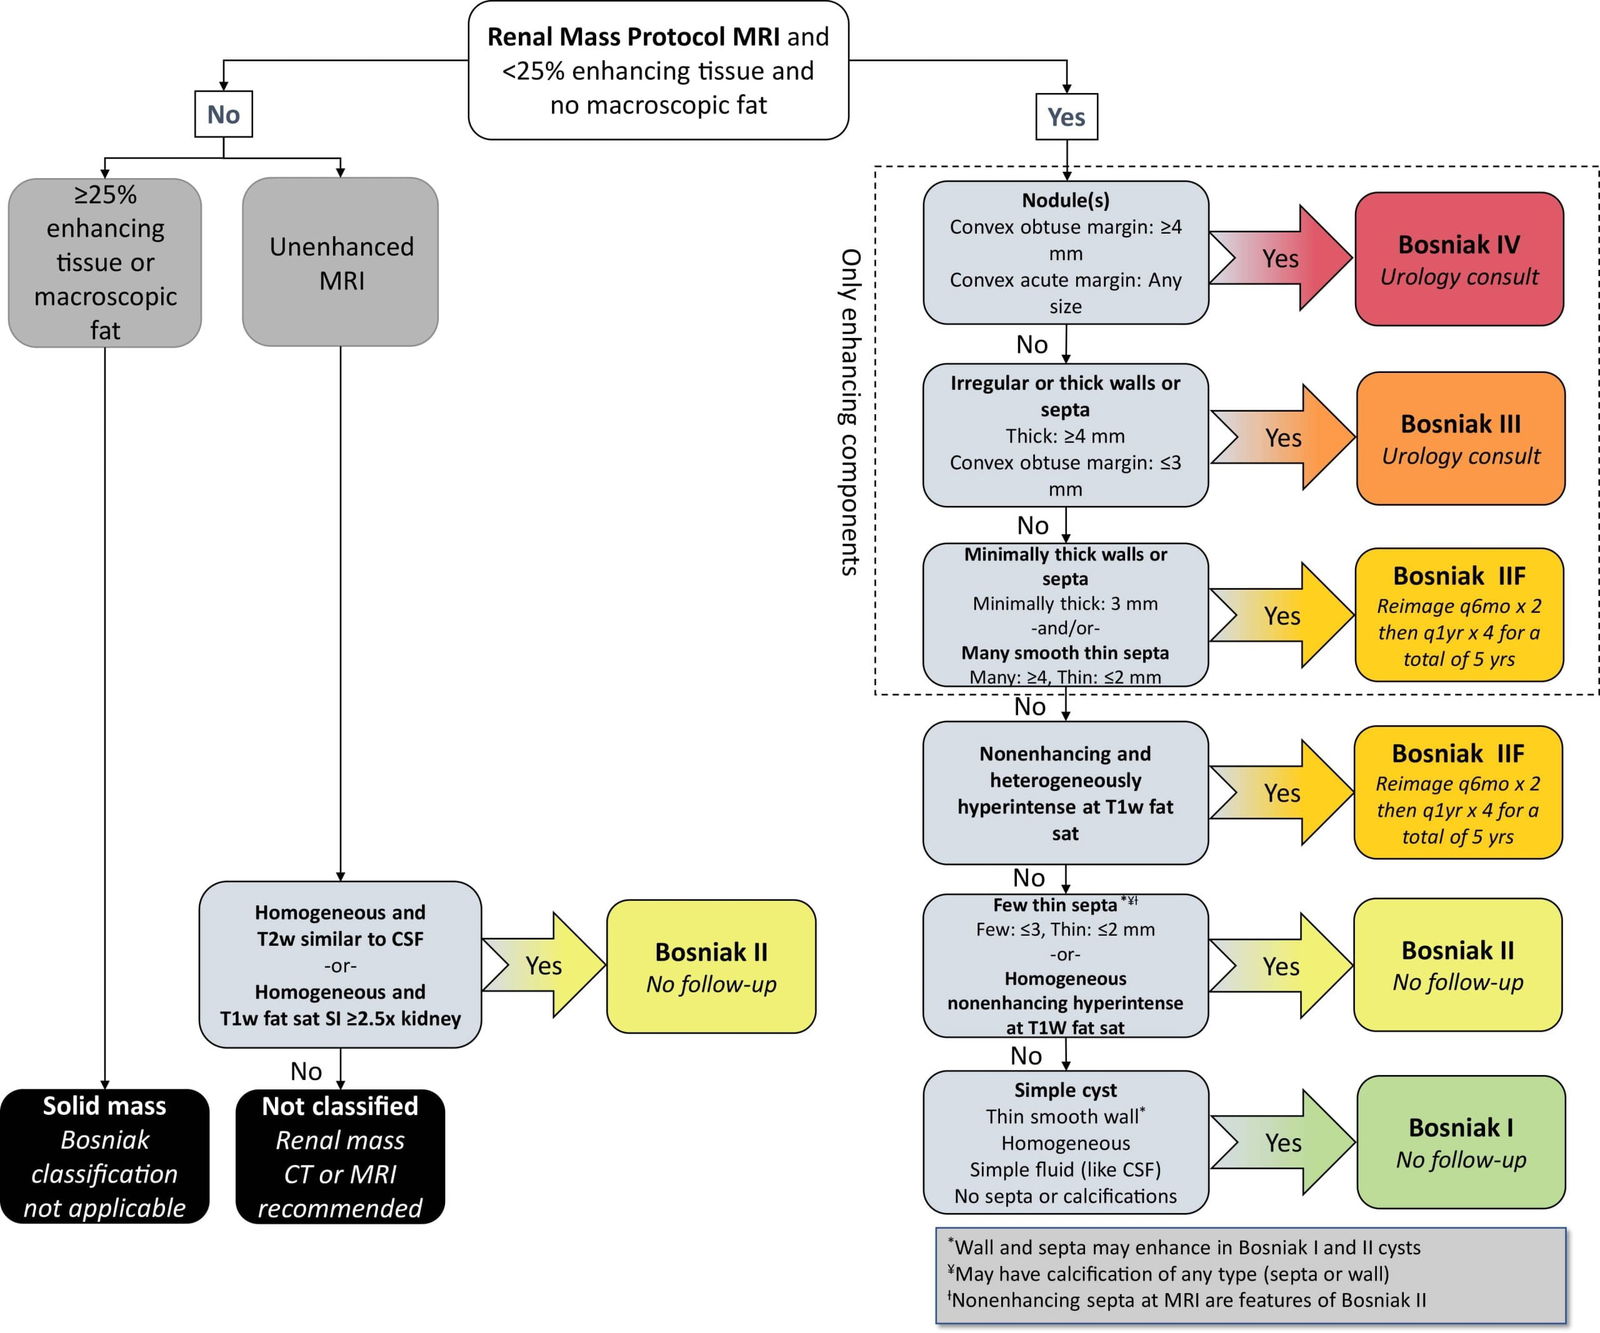
The calculator above walks through the v2019 decision tree. The sections below give the criteria, the current malignancy figures from the 2025 meta-analysis, the follow-up recommendations, and the pitfalls that most often produce a wrong class.
Bosniak v2019 Criteria on CT and MRI
A mass must first qualify for the system at all: it has to be a well-defined renal mass with less than 25% enhancing tissue, no macroscopic fat, and no infiltrative appearance, imaged with a dedicated renal mass protocol. Everything else is graded as below.
| Class | CT criteria | MRI criteria |
|---|---|---|
| I | Well defined, thin (≤2 mm) smooth enhancing or non-enhancing wall; homogeneous simple fluid (−9 to 20 HU); no septa; no calcification | Well defined, thin (≤2 mm) smooth wall; homogeneous simple fluid signal (markedly T2 hyperintense, similar to CSF); no septa or calcification |
| II | Thin (≤2 mm) smooth wall plus any one of: few (1–3) thin enhancing septa; homogeneous hyperattenuating mass ≥70 HU on non-contrast CT; homogeneous non-enhancing mass >20 HU on renal mass protocol CT; homogeneous mass −9 to 20 HU on non-contrast CT; homogeneous mass 21–30 HU on portal venous phase CT; homogeneous low-attenuation mass too small to characterise. Calcification of any type is allowed | Homogeneous mass markedly hyperintense on T2 (similar to CSF) without contrast; homogeneous mass markedly hyperintense on T1 (about 2.5 times normal parenchymal signal) without contrast; few (1–3) thin enhancing septa |
| IIF | Smooth minimally thickened (3 mm) enhancing wall, or smooth minimal thickening (3 mm) of one or more enhancing septa, or many (≥4) smooth thin (≤2 mm) enhancing septa | Same wall and septal criteria as CT, plus masses that are heterogeneously hyperintense on unenhanced fat-saturated T1-weighted imaging |
| III | One or more enhancing thick (≥4 mm) walls or septa, or enhancing irregular walls or septa (obtusely marginated convex protrusion ≤3 mm) | Same as CT |
| IV | One or more enhancing nodules: a convex protrusion ≥4 mm with obtuse margins, or a convex protrusion of any size with acute margins | Same as CT |
The three measurements that decide the class
| Term | v2019 definition | Why it matters |
|---|---|---|
| Thin | ≤2 mm | Thin walls and septa may enhance and still be class I or II |
| Minimally thickened | 3 mm | Single feature that defines class IIF |
| Thick | ≥4 mm | Defines class III |
| Few septa | 1–3 | Class II |
| Many septa | ≥4 (smooth, thin) | Class IIF |
| Irregularity | Obtusely marginated convex protrusion ≤3 mm | Class III |
| Nodule | Obtuse protrusion ≥4 mm, or acute-margined protrusion of any size | Class IV |
Note the change that catches most readers out: calcification no longer upgrades a mass. Calcification of any type or thickness is permitted in class II. It matters only when it is abundant enough to obscure assessment of enhancement, in which case the mass is not classified and MRI is recommended instead.
Risk of Malignancy by Bosniak Class
The figures below come from a 2025 systematic review and meta-analysis in AJR that pooled 12 studies, 966 patients and 975 cystic masses classified with v2019 — the largest synthesis of v2019 data to date. They replace the older v2005-era percentages that are still widely quoted.
| Class | Pooled malignancy (v2019) | 95% CI | Practical reading |
|---|---|---|---|
| I | 0% | — | No class I mass was malignant in the pooled cohort |
| II | 9% | 5–17% | Higher than the historically quoted <1%, largely because surgical series over-represent malignant masses |
| IIF | 26% | 13–46% | Highly reference-standard dependent — see the caveat below |
| III | 80% | 71–87% | Substantially higher than the ~50% usually quoted from v2005 data |
| IV | 88% | 83–91% | Consistent with historical figures |
Read class II and IIF with care. In the same meta-analysis, IIF masses that went to histopathology were malignant in 41% of cases, but IIF masses followed with imaging were malignant in only 2%. That gap is verification bias: masses only get resected when something about them worries the clinician, so surgical series systematically overstate risk. The imaging-follow-up figure is the one that describes the average IIF cyst reported in daily practice.
Malignancy by v2019 subclass
The 2019 revision defines each class by a specific feature, and the meta-analysis shows those features do not carry equal risk. This is useful when deciding how firmly to word a report.
| Class | Defining feature | Pooled malignancy | 95% CI |
|---|---|---|---|
| IIF | Many (≥4) smooth thin septa | 10% | 2–33% |
| IIF | Minimal wall or septal thickening (3 mm) | 47% | 18–77% |
| IIF | Heterogeneous T1 hyperintensity (MRI) | 26% | 8–57% |
| III | Thick, smooth wall or septa (≥4 mm) | 78% | 60–90% |
| III | Obtuse protrusion ≤3 mm | 84% | 77–90% |
| IV | Acute-margined protrusion of any size | 88% | 80–93% |
| IV | Obtuse protrusion ≥4 mm | 86% | 77–91% |
Two practical points fall out of this table. A IIF cyst that is IIF only because it has many thin septa carries roughly a tenth the risk of one that is IIF because of 3 mm thickening — the label is the same, the lesion is not. And the two class III subclasses and the two class IV subclasses overlap heavily, which is why the III versus IV distinction changes management much less than the II versus III one.
Management and Follow-Up by Bosniak Class
| Class | Recommended management | Notes |
|---|---|---|
| I | Benign. No follow-up imaging. | Report as a simple cyst; no need to describe it as indeterminate |
| II | Benign. No follow-up imaging. | Includes hyperattenuating and calcified cysts that used to trigger surveillance under v2005 |
| IIF | Imaging surveillance: CT or MRI at 6 and 12 months, then annually to a total of 5 years. | Most remain stable. Progression after 3 years is rare |
| III | Urology referral. Options include partial nephrectomy, thermal ablation or active surveillance. | Active surveillance is now an accepted option in selected patients |
| IV | Urology referral. Treatment (usually partial nephrectomy) is generally indicated. | Highest malignancy rate; when malignant, most are low-grade clear cell RCC |
Surveillance is safer than it once looked. In a series of 532 patients followed for a median of 66 months, active surveillance of Bosniak IIF and III masses gave a 5-year metastasis-free survival of 98.9% and cancer-specific survival of 99.6%, with no significant difference from immediate surgery. Surgery remained the primary treatment for class IV. The 2025 EAU renal cell carcinoma guideline likewise supports surveillance as an option for small, low-risk renal masses.
Biopsy has a limited role in cystic masses. A 2026 meta-analysis of percutaneous sampling in Bosniak III–IV cysts (7 studies, 954 patients) found fine-needle aspiration pooled sensitivity of only 59% with specificity of 84%. A negative result does not exclude malignancy, so a negative biopsy should not by itself downgrade a class III or IV mass.
Bosniak 2005 vs Bosniak 2019: What Actually Changed
| Feature | Bosniak v2005 | Bosniak v2019 |
|---|---|---|
| Modalities | CT (MRI used informally) | CT and MRI, with explicit MRI criteria |
| Wall and septal thickness | Subjective (‘hairline thin’, ‘thickened’) | Numeric: thin ≤2 mm, minimally thickened 3 mm, thick ≥4 mm |
| Number of septa | ‘Multiple’ septa, undefined | Few = 1–3; many = ≥4 |
| Calcification | Thick or nodular calcification upgraded the mass | Calcification of any type allowed in class II; does not upgrade |
| Enhancement | ‘Perceived’ versus ‘measurable’ enhancement | Enhancement of thin walls and septa is permitted in class I and II |
| Nodule | Undefined ‘enhancing soft-tissue component’ | Defined by geometry: obtuse ≥4 mm, or acute margin at any size |
| Solid component limit | Not specified | Mass must have <25% enhancing tissue to be classified |
| Net effect | More masses called IIF and III | Many masses downgraded to class II; fewer surveillance and surgical referrals |
The size of that shift is well documented. Applying v2019 retrospectively to 181 Bosniak IIF cysts produced a 76% reduction in IIF diagnoses, with no increase in class III or IV diagnoses and identical classification of the one confirmed malignancy. In that cohort only 2.2% of IIF cysts progressed, and no malignant progression occurred after 36 months.
Reader agreement also improved. In a 207-patient MRI series, interobserver agreement rose from a weighted kappa of 0.50 with v2005 to 0.64 with v2019, and specificity for malignancy rose from 68% to 83% with no loss of sensitivity (84% to 89%). Agreement with v2019 was the same for junior and senior readers, which was not true of v2005 — the objective thresholds do the work that experience used to. Results have not been uniformly positive: a resident-reader study found only fair-to-moderate agreement with both versions, so structured training still matters.
Can You Use Bosniak on Ultrasound?
No — not formally. Bosniak v2019 applies to renal mass protocol CT and MRI only. Greyscale ultrasound cannot demonstrate enhancement, which is the pivot on which most of the classification turns, so a cyst seen only on ultrasound should be described morphologically and characterised with CT or MRI if it is not a simple cyst.
Contrast-enhanced ultrasound (CEUS) is a different matter and is used in practice, particularly where iodinated contrast or gadolinium is contraindicated. CEUS resolves septal and nodular perfusion very well, with no ionising radiation and no nephrotoxicity. In a prospective series of 40 cystic renal masses, CEUS reached 100% sensitivity and 100% negative predictive value for malignancy, but only 73.9% specificity, against 88.2% sensitivity and 87% specificity for contrast-enhanced CT. That asymmetry is the point: CEUS shows thin septa and faint perfusion that CT misses, so it tends to upgrade masses. A CEUS class and a CT class are therefore not interchangeable. Report the modality alongside the class, and be explicit that CEUS grading is an extension of the system rather than part of v2019.
Pitfalls That Cause a Wrong Bosniak Class
| Pitfall | What goes wrong | How to avoid it |
|---|---|---|
| Pseudoenhancement | Small (<1.5 cm) intraparenchymal cysts appear to enhance by 10–20 HU from beam-hardening and reconstruction effects, prompting a false class III or IV | Suspect it in small, completely intrarenal cysts. Dual-energy CT with iodine maps, or MRI with subtraction, settles it |
| Hyperattenuating masses 20–70 HU | Indeterminate on a single-phase study — most are haemorrhagic or proteinaceous cysts but some are solid masses | Homogeneous mass ≥70 HU on true non-contrast CT is a benign cyst. Between 20 and 70 HU, do renal mass protocol CT or MRI |
| Single portal venous phase CT | Enhancement cannot be assessed, so a complex cyst is called indeterminate or overcalled | A homogeneous mass of 21–30 HU on portal venous phase is class II. Otherwise repeat with a multiphase renal mass protocol |
| Measuring a protrusion obliquely | The 3 mm versus 4 mm boundary between class III and IV is missed | Measure perpendicular to the wall or septum, and assess the margin angle before the size |
| Grading a mass with ≥25% enhancing tissue | The mass is a solid renal mass with cystic or necrotic change, not a cystic mass | Bosniak does not apply — report as a solid renal mass and refer |
| Applying Bosniak in hereditary syndromes | In von Hippel-Lindau and other hereditary RCC syndromes, class I and II cysts can harbour malignancy | Do not apply the classification; follow syndrome-specific surveillance |
| Applying Bosniak to infection or infarction | Abscesses, infected cysts and infarcts can look like class III or IV masses | Exclude an infectious, inflammatory or vascular cause first; re-image after treatment |
| Abundant nodular calcification | Calcification masks enhancement on CT and makes the class unassignable | Do not classify on CT — recommend MRI |
How to Use This Bosniak Calculator
A short animated walk-through of the v2019 classification itself:

Bosniak Classification FAQs
What is the Bosniak classification?
The Bosniak classification is a five-tier system (I, II, IIF, III, IV) that grades a cystic renal mass on CT or MRI according to how likely it is to be malignant. Class I and II are benign and need no follow-up, class IIF is followed with imaging, and class III and IV are referred to urology. The current version is Bosniak version 2019.
What is a Bosniak IIF cyst and does it need follow-up?
A Bosniak IIF cyst has either a smooth minimally thickened (3 mm) enhancing wall or septum, or many (four or more) smooth thin enhancing septa. It is followed with CT or MRI at 6 and 12 months and then annually to 5 years. Most stay stable: in one series only 2.2 percent progressed and none progressed after 36 months.
What is the malignancy rate of each Bosniak class?
In a 2025 meta-analysis of 975 masses graded with version 2019, pooled malignancy was 0 percent for class I, 9 percent for class II, 26 percent for class IIF, 80 percent for class III and 88 percent for class IV. The class IIF figure depends heavily on the reference standard: 41 percent when confirmed by surgery, but only 2 percent when followed by imaging.
What is the difference between Bosniak 2005 and Bosniak 2019?
Version 2019 replaced subjective wording with measured thresholds (thin is 2 mm or less, minimally thickened is 3 mm, thick is 4 mm or more), defined few septa as 1 to 3 and many as 4 or more, added explicit MRI criteria, stopped upgrading masses for calcification, and defined a nodule by its margin angle and size. In practice it downgrades many masses: applied retrospectively it reduced Bosniak IIF diagnoses by 76 percent.
Does calcification change the Bosniak class?
No. Under version 2019 calcification of any type or thickness is allowed in a class II cyst and does not upgrade it. Calcification matters only when it is abundant enough to obscure assessment of enhancement, in which case the mass should not be classified on CT and MRI is recommended.
What is the difference between Bosniak III and Bosniak IV?
Class III has an enhancing thick wall or septum (4 mm or more) or an irregular wall or septum, defined as an obtusely marginated convex protrusion of 3 mm or less. Class IV has an enhancing nodule: a convex protrusion of 4 mm or more with obtuse margins, or a protrusion of any size with acute margins. Pooled malignancy is 80 percent for class III and 88 percent for class IV, so both are referred to urology.
Can the Bosniak classification be used on ultrasound?
Not formally. Version 2019 applies only to renal mass protocol CT and MRI, because greyscale ultrasound cannot show enhancement. Contrast-enhanced ultrasound is used in practice, particularly when iodinated contrast or gadolinium is contraindicated, but it is more sensitive to thin septa and tends to upgrade masses relative to CT, so the modality should always be stated with the class.
When should the Bosniak classification not be applied?
Do not apply it to a mass with 25 percent or more enhancing tissue or macroscopic fat, to lesions with an infectious, inflammatory or vascular cause, to cysts in hereditary renal cancer syndromes such as von Hippel-Lindau where benign-looking cysts can be malignant, or to a mass whose enhancement cannot be assessed because of abundant calcification.
Related Radiology Calculators
- ACR TI-RADS calculator for thyroid nodules
- O-RADS ultrasound calculator for adnexal lesions
- LI-RADS calculator for liver observations
- RENAL nephrometry score calculator for surgical planning of a renal mass
- Radiology volume calculator for lesion and organ volumes
- All RadioGyan radiology calculators
Disclaimer: This calculator and article are for educational use by clinicians and are not a substitute for the full published criteria or for clinical judgment.
References
- Silverman SG, Pedrosa I, Ellis JH, et al. Bosniak Classification of Cystic Renal Masses, Version 2019: An Update Proposal and Needs Assessment. Radiology. 2019;292(2):475-488. PMID: 31210616.
- McGrath TA, Bhatt GM, Nikpanah M, et al. Bosniak Classification of Cystic Renal Masses Version 2019: Proportion of Malignancy by Class and Subclass — Systematic Review and Meta-Analysis. AJR Am J Roentgenol. 2025;224(3):e2432342. PMID: 39772585.
- Bai X, Sun SM, Xu W, et al. MRI-based Bosniak Classification of Cystic Renal Masses, Version 2019: Interobserver Agreement, Impact of Readers’ Experience, and Diagnostic Performance. Radiology. 2020;297(3):597-605. PMID: 32960726.
- Couture F, Nguyen DD, Bhojani N, et al. Evolution of Bosniak IIF Renal Cysts and Impact of the 2019 Bosniak Classification. J Urol. 2023;209(4):694-700. PMID: 36573917.
- Yan JH, Chan J, Osman H, et al. Bosniak Classification version 2019: validation and comparison to original classification in pathologically confirmed cystic masses. Eur Radiol. 2021;31(12):9579-9587. PMID: 34019130.
- Luomala L, Rautiola J, Sankila A, et al. Active surveillance versus initial surgery in the long-term management of Bosniak IIF-IV cystic renal masses. Sci Rep. 2022;12(1):10184. PMID: 35715428.
- Narayanasamy S, Krishna S, Prasad Shanbhogue AK, et al. Contemporary update on imaging of cystic renal masses with histopathological correlation and emphasis on patient management. Clin Radiol. 2019;74(2):83-94. PMID: 30314810.
- Bex A, Albiges L, Bedke J, et al. European Association of Urology Guidelines on Renal Cell Carcinoma: The 2025 Update. Eur Urol. 2025;87(6):683-696. PMID: 40118739.
- Schieda N, Davenport MS, Krishna S, et al. Bosniak Classification of Cystic Renal Masses, Version 2019: A Pictorial Guide to Clinical Use. RadioGraphics. 2021;41(3):814-828. PMID: 33861647.
- Edney E, Davenport MS, Curci N, et al. Bosniak classification of cystic renal masses, version 2019: interpretation pitfalls and recommendations to avoid misclassification. Abdom Radiol (NY). 2021;46(6):2699-2711. PMID: 33484283.
- Das CJ, Agarwal K, Sharma S, et al. Role of Contrast-Enhanced Ultrasound in Evaluation of Cystic Renal Mass. J Ultrasound Med. 2023;42(12):2873-2881. PMID: 37676901.
- Abufaraj M, Alhanbali YE, Al-Qalalweh SB, et al. Interrater agreement and reliability of the Bosniak classification for cystic renal masses version 2019. Urol Oncol. 2025;43(3):192.e1-192.e10. PMID: 39462756.
- Barretta A, Mottaran A, Carl N, et al. Diagnostic value of percutaneous sampling in Bosniak III-IV renal cysts: a systematic review and meta-analysis. Can J Urol. 2026;33(4):783-793. PMID: 42682044.
Improve Content And Help Your Colleagues!
Found an error in the post? Please let us know using our contact page and we will update it with due credits!
If you wish to contribute radiological images for this case (or any other article on the website), you can submit them here and you will be duly credited: Submit radiology case
About the Author
Dr. Amar Udare, MD, DNB
Dr. Udare holds an MBBS and MD degree, and his expertise lies in the field of radiology. He has authored multiple peer-reviewed publications, contributing significantly to the medical field. His works can be accessed on PubMed and Google Scholar.
In addition to his academic and professional achievements, Dr. Udare is an avid reader and enjoys exploring the latest advancements in medical technology. His commitment to making complex medical knowledge accessible to patients and the general public aligns with our mission at RadioGyan.com.
For any further questions or clarifications, feel free to reach out to Dr. Udare via the contact form.