


What causes colon cut-off sign in the colon on abdominal radiographs or computed tomography?
Let me know in the comments.
Click to reveal the answer
The colon cut-off sign is an abrupt stop to colonic gas at the splenic flexure, with a gas-filled colon proximally and a collapsed, gasless colon beyond it. It is focal colonic ileus next to an inflamed pancreas, not mechanical obstruction. It is classically taught for acute pancreatitis, but it is uncommon and it is not specific.
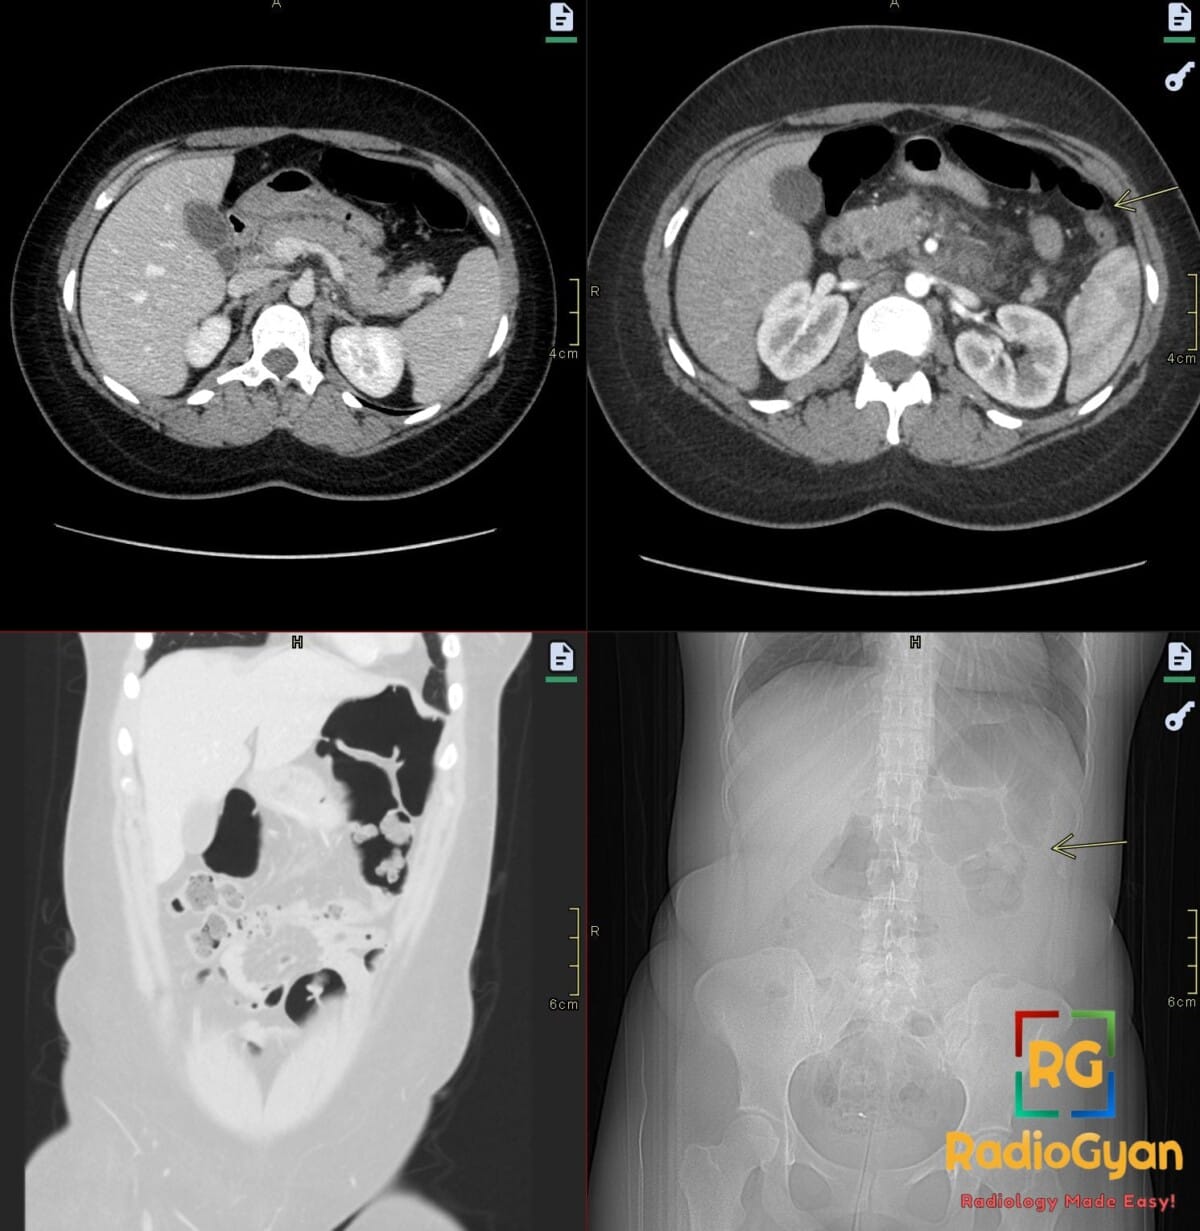
Why is it called so?
The gas column looks sliced off at the splenic flexure: distended colon on one side, empty colon on the other. The sign has carried this name in the radiology literature since at least 1956 [1] and has been written up under it ever since. [2] [3] The term describes a gas pattern, not a disease.
Pathophysiology
Pancreatic exudate escapes the gland and tracks along the transverse mesocolon and the phrenicocolic ligament, which anchor the colon at the splenic flexure. That segment stops propelling its contents, so gas collects proximally while the colon beyond the flexure empties. Reviewers classify the sign as a localised paralytic ileus and attribute it to enzymatic, inflammatory and ischaemic processes. [4] The anatomical route itself is classical teaching that no indexed study quantifies.
Alternative names: colon cutoff sign, colonic cut-off sign, splenic flexure cut-off sign.
Other associated named signs: sentinel loop sign, gasless abdomen, and the dilated transverse colon of acute pancreatitis.
How often is the colon cut-off sign actually seen?
Less often than the teaching implies. One study read the radiographs of 100 patients who had acute pancreatitis against 100 controls, specifically to test how useful the published plain-film signs were, and the cut-off sign was not seen in those 100 radiographs. [5] Its ranking of the useful signs runs duodenal loop distension, gas in the duodenal cap, a dilated transverse colon, then the sentinel loop. The colon cut-off sign is not on the list. [5] Later authors note only that the reported frequency and sensitivity of the sign fluctuate considerably between studies, without giving figures. [6] No sensitivity or specificity for the sign in pancreatitis appears in any indexed abstract.
| Plain-film finding in acute pancreatitis | What the controlled series reported |
|---|---|
| Colon cut-off sign | Not seen in the 100 radiographs reviewed |
| Dilated transverse colon | 18%, and the most constant colonic sign |
| Adynamic duodenal loop outlined by gas | Half of those filmed in the left lateral decubitus position |
| Dilated jejunum | 31 cases, with sentinel loops in 10 of them |
| Gasless abdomen | Striking but rare, and here always with severe pancreatitis |
What else causes a colon cut-off sign?
It is not specific to pancreatitis, and it is not confined to the splenic flexure. Anything that inflames or bleeds into the tissues alongside the colon can arrest the gas column there.
| Cause | What is actually published |
|---|---|
| Acute pancreatitis, including mild and oedematous disease | The classical association, documented on CT and on the CT scout image [6] [7] |
| Ureteral rupture from an obstructing calculus | A radiograph showed gas stopping at the splenic flexure; CT found the ruptured ureter [8] |
| Gastric cancer, splenic artery bleeding, ruptured abdominal aortic aneurysm | Listed among reported causes in a case report, without cases or citations given [7] |
| Paediatric appendicitis | A cut-off sign at the hepatic flexure is one of six plain-film findings used to suggest perforation [9] |
| Walled-off pancreatic necrosis with true mechanical obstruction | Rare, but it carries high morbidity and mortality, and it is a different problem from focal ileus [10] |
Why it matters: an alarm, not a diagnosis
The sign itself is benign. A review of 432 published cases of colonic involvement in pancreatitis found that the cut-off sign is almost always spontaneously reversible, and that its value is as an alarm for the colonic complications that are not: necrosis, fistula, stenosis and varices. [4] It says nothing about severity, since a localised ileus of the transverse colon appears even when the pancreatitis is mild. [10] It also cuts both ways at the flexure: a post-pancreatitis colonic stenosis can mimic carcinoma clinically, [4] and in one reported case a stenosis there halted a colonoscopy on suspicion of a stenosing tumour before CT showed pancreatitis. [6]
How to handle it in a report
- Name the transition point. The level, usually the splenic flexure, is the only information
the sign carries. - Call it focal colonic ileus, not obstruction, on a plain film alone.
- Check the CT scout image as well as the axial slices: the whole gas column is visible at
once there, and the scout has been the image that made the diagnosis. [7] - If the clinical picture does not fit pancreatitis, work through the other causes and
consider CT. Conventional radiography is often the first study requested for abdominal pain
and cannot give a confident diagnosis on its own. [8]
Colon cut-off sign versus sentinel loop sign
Both are focal ileus beside an inflamed pancreas, which is why they are confused and why they are so often asked together. They differ in the bowel involved and in the appearance. The companion sign is covered in full in our article on the sentinel loop sign.
| Colon cut-off sign | Sentinel loop sign | |
|---|---|---|
| Bowel involved | Colon | Small bowel, usually duodenum or jejunum |
| Appearance | Gas stops abruptly, gasless colon beyond | One short dilated loop that holds its position |
| Usual site | Splenic flexure | Beside whichever organ is inflamed |
| In the 100-patient series | Not seen [5] | Sentinel loops in 10 of the 31 patients with a dilated jejunum [5] |
Frequently asked questions
Which condition is the colon cut-off sign seen in?
Acute pancreatitis is the classical answer and the one examinations expect. The sign has also been reported with ureteral rupture, gastric cancer, splenic artery bleeding, a ruptured abdominal aortic aneurysm and paediatric appendicitis, so it indicates inflammation beside the colon rather than one disease.
Is the colon cut-off sign specific for acute pancreatitis?
No. No sensitivity or specificity for it has been published in any indexed abstract, its reported frequency varies widely between studies, and the one series that compared 100 patients who had acute pancreatitis with 100 controls did not see the sign in those 100 radiographs.
Can the colon cut-off sign be seen on CT?
Yes, on axial CT and often most clearly on the CT scout or scanogram image, where the whole gas column is visible at once. A scout image showing the sign has been the finding that led to the diagnosis of acute pancreatitis in reported cases.
What is the difference between the colon cut-off sign and the sentinel loop sign?
The colon cut-off sign is colonic: gas stops abruptly, usually at the splenic flexure, with no gas beyond it. The sentinel loop sign is in the small bowel: one short dilated loop sits beside the inflamed organ and keeps its position on serial films.
References
- Price CW. The colon cut-off sign in acute pancreatitis. Med J Aust. 1956;43(8):313-4. PMID: 13308557. PubMed
- Brascho DJ, Reynolds TN, Zanca P. The radiographic “colon cut-off sign” in acute pancreatitis. Radiology. 1962;79:763-9. PMID: 14015002. PubMed
- Pickhardt PJ. The colon cutoff sign. Radiology. 2000;215(2):387-9. PMID: 10796912. PubMed
- Negro P, D’Amore L, Saputelli A, Talarico C, Scaccia M, Tuscano D, Gossetti F, Carboni M. Colonic lesions in pancreatitis. Ann Ital Chir. 1995;66(2):223-31. PMID: 7668499. PubMed
- Davis S, Parbhoo SP, Gibson MJ. The plain abdominal radiograph in acute pancreatitis. Clin Radiol. 1980;31(1):87-93. PMID: 7357829. PubMed
- Schrum A, Scheer F, Andresen R. Colon-cut-off-sign in the CT-scanogram: evidence of pancreatitis? J Clin Diagn Res. 2015;9(11):TD01-2. PMID: 26675990. PubMed
- Shinomiya R, Inoue N, Kawamura T, Uno K. Acute pancreatitis with colon cutoff sign. Clin Case Rep. 2023;11(10):e8086. PMID: 37867544. PubMed
- Liao MT, Chang WC, Tsai SH, Huang GS, Yu CY. The colon cutoff sign: an unusual indicator of urologic disease. Urology. 2008;71(6):1052. PMID: 18436281. PubMed
- Johnson JF, Coughlin WF, Stark P. The sensitivity of plain films for detecting perforation in children with appendicitis. Rofo. 1988;149(6):619-23. PMID: 2849160. PubMed
- Bassi M, Desai A, Pitchumoni CS. Recurrent large bowel obstruction caused by necrotizing pancreatitis: a rare manifestation. Cureus. 2020;12(12):e12307. PMID: 33520506. PubMed
Access all radiology signs posted so far: https://radiogyan.com/radiology-signs/

Improve Content And Help Your Colleagues!
Found an error in the post? Please let us know using our contact page and we will update it with due credits!
If you wish to contribute radiological images for this case (or any other article on the website), you can submit them here and you will be duly credited: Submit radiology case