

What causes a rachitic rosary on the chest radiograph?
Let me know in the comments.
Click to reveal the answer
Answer:
A rachitic rosary is bulbous beading of the anterior rib ends at the costochondral junctions in rickets. Unmineralised cartilage and osteoid pile up at each junction, so the rib end widens, cups and loses its sharp margin. The beads are palpable and visible on a frontal chest radiograph beside the sternum.
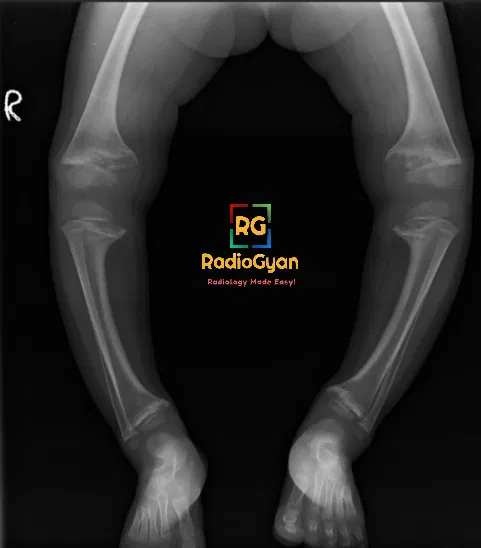
The costochondral junction is a growth plate, and it fails the way every other growth plate fails in rickets [3]. So a rosary is rarely isolated: look for metaphyseal fraying, cupping and splaying at the wrist and knee, a widened growth plate, coarse trabeculation, generalised osteopenia, bowing of the long bones, Looser zones, frontal bossing, craniotabes and the Harrison sulcus. The rosary raises the question; the wrist or knee radiograph and the biochemistry answer it [2].
Why is it called so?
The row of rounded swellings along the costochondral junctions resembles a string of rosary beads running down each side of the sternum.
Pathophysiology
Deficient vitamin D, calcium or phosphate prevents mineralisation of newly formed osteoid at every growth plate [1]. At the costochondral junction the hypertrophic chondrocyte zone keeps proliferating while the new cartilage fails to mineralise, so unmineralised cartilage and osteoid accumulate and the junction expands laterally. The result is a bulbous, mechanically soft rib end that is both palpable and radiographically enlarged. The same failure at the long bone metaphyses produces the widened growth plates and frayed metaphyses seen at the sites of fastest growth [3], and the softened diaphyses bow under load.
Alternative names: Rachitic beads, rickety rosary, beading of the ribs
Other associated named signs: Scorbutic rosary, Harrison sulcus, Looser zones, metaphyseal fraying and cupping, and the Wimberger ring sign of scurvy
Rachitic rosary versus scorbutic rosary
Scurvy beads the costochondral junctions too, so the row of beads does not separate the two. Look instead at the density of the bone just behind the junction. Rickets fails to mineralise it, so the rib end is lucent, frayed and indistinct [3]. Scurvy lays down a dense band, the white line of Frankel, with a lucent zone immediately behind it [7][8].
| Feature | Rachitic rosary (rickets) | Scorbutic rosary (scurvy) |
|---|---|---|
| Primary defect | Osteoid is laid down but cannot mineralise | Vitamin C deficiency impairs collagen synthesis, so little matrix is made |
| Metaphyseal density | Lucent and indistinct | Dense band (Frankel line) with a lucent zone behind it |
| Rib end margin | Rounded, cupped, frayed | Sharper, more angular, with a step-off |
| Metaphyseal shape | Widened, cupped, splayed | Width largely preserved |
| Companion signs | Fraying and splaying, bowing, Looser zones, Harrison sulcus | Wimberger ring, Pelkan spur, Trummerfeld zone, subperiosteal haemorrhage [7] |
How often is the rosary actually there?
More often than the textbooks imply in children who have rickets, and almost never in children who do not. Among 21 Kenyan children aged 3 to 24 months with rickets, a rachitic rosary was present in 90% (19 of 21), second only to wrist widening at 100% [5]. In 19 Vietnamese children with vitamin D dependent rickets type 1A it was present in 63% (12 of 19) [6]. Both series are small and single centre, so treat them as an order of magnitude, not a published sensitivity.
The converse matters more for everyday reporting. Among 79 infants and toddlers imaged for fractures, suboptimal vitamin D was common but radiographic rickets was not, and none showed a rachitic rosary, Looser zones or metaphyseal change [9]. A rosary is a finding of established rickets, not a screening sign for vitamin D deficiency.
The rest of the rachitic chest
Rickets softens the whole thoracic cage. The Harrison sulcus is a horizontal groove along the lower chest at the costal insertion of the diaphragm, usually explained by diaphragmatic traction on ribs too soft to resist it. It is a surface contour seen on examination rather than a radiographic sign, and it is not specific to rickets: chronic respiratory disease and malnutrition produce it too.
- Rachitic rosary: beaded anterior rib ends, best seen on the frontal film beside the sternum.
- Harrison sulcus: horizontal indrawing at the diaphragmatic insertion, a clinical sign.
- Generalised osteopenia with coarse, indistinct trabeculae.
- Worth a look on every paediatric chest film: among 221 children admitted with severe pneumonia in Uganda, 9.5% had radiographic rickets [10].
- Confirm elsewhere: radiograph the wrist or knee, where the growing metaphysis shows the changes most clearly [2].
A rosary is not always nutritional
Vitamin D deficiency is much the commonest cause [1], but any disorder that blocks mineralisation at the growth plate can produce the same rib ends. Vitamin D dependent rickets type 1A is the best documented non-nutritional example [6]. The distinction matters because the treatment differs: phosphate wasting does not respond to vitamin D alone.
- Nutritional rickets: vitamin D deficiency, dietary calcium deficiency, or both [1].
- Vitamin D dependent rickets: defects of vitamin D activation or receptor signalling [6].
- X-linked hypophosphataemic rickets: renal phosphate wasting driven by FGF23. Severity is graded on the same wrist and knee radiographs [4].
- Renal osteodystrophy in chronic kidney disease.
- Metabolic bone disease of prematurity.
Frequently asked questions
What is the difference between a rachitic rosary and a scorbutic rosary?
Both are beaded costochondral junctions, so shape alone will not separate them. Look at the density of the bone behind the junction. In rickets it fails to mineralise, so it is lucent, frayed and indistinct. In scurvy there is a dense white line (the Frankel line) with a lucent zone immediately behind it, and the companion signs are the Wimberger ring, Pelkan spurs and subperiosteal haemorrhage.
Where is the rachitic rosary seen and felt?
At the anterior costochondral junctions, as a row of beads running down each side of the sternum. It is palpable on examination and visible on a frontal chest radiograph as bulbous expansion of the anterior rib ends.
Is a rachitic rosary enough to diagnose rickets?
No. It raises the suspicion. Diagnosis rests on radiographs of a rapidly growing growth plate, the wrist or the knee, showing metaphyseal fraying and a widened growth plate, together with the biochemistry. A rosary noticed on a chest film ordered for another reason should prompt both.
What is the Harrison sulcus?
A horizontal depression along the lower chest where the diaphragm inserts into the ribs, usually attributed to diaphragmatic traction on softened ribs. It is a clinical contour rather than a radiographic sign, and chronic respiratory disease and malnutrition can produce it without rickets.
References
- Munns CF, Shaw N, Kiely M, et al. Global Consensus Recommendations on Prevention and Management of Nutritional Rickets. J Clin Endocrinol Metab. 2016;101(2):394-415. PMID: 26745253.
- Haffner D, Leifheit-Nestler M, Grund A, et al. Rickets guidance: part I, diagnostic workup. Pediatr Nephrol. 2022;37(9):2013-2036. PMID: 34910242.
- Chang CY, Rosenthal DI, Mitchell DM, et al. Imaging Findings of Metabolic Bone Disease. Radiographics. 2016;36(6):1871-1887. PMID: 27726750.
- Thacher TD, Fischer PR, Pettifor JM, et al. Radiographic scoring method for the assessment of the severity of nutritional rickets. J Trop Pediatr. 2000;46(3):132-139. PMID: 10893912.
- Jones KDJ, Hachmeister CU, Khasira M, et al. Vitamin D deficiency causes rickets in an urban informal settlement in Kenya and is associated with malnutrition. Matern Child Nutr. 2018;14(1):e12452. PMID: 28470840.
- Tran TAT, Dien TM, Nguyen NL, et al. Phenotypes and Genotypes of Children with Vitamin D-Dependent Rickets Type 1A: A Single Tertiary Pediatric Center in Vietnam. Diagnostics (Basel). 2025;15(7):817. PMID: 40218268.
- Susilo F, Clarissa S, Handoyono QF, et al. A case report of a childhood scurvy musculoskeletal manifestation: Radiologic findings and diagnostic implications. Radiol Case Rep. 2024;19(8):3235-3239. PMID: 38800077.
- Golriz F, Donnelly LF, Devaraj S, et al. Modern American scurvy, experience with vitamin C deficiency at a large children’s hospital. Pediatr Radiol. 2017;47(2):214-220. PMID: 27778040.
- Servaes S, States L, Wood J, et al. Rachitic change and vitamin D status in young children with fractures. Skeletal Radiol. 2020;49(1):85-91. PMID: 31243488.
- Piloya T, Odongkara B, Were EM, et al. Nutritional rickets among children admitted with severe pneumonia at Mulago hospital, Uganda: a cross-sectional study. BMC Pediatr. 2018;18(1):336. PMID: 30373538.
Access all radiology signs posted so far: https://radiogyan.com/radiology-signs/
Improve Content And Help Your Colleagues!
Found an error in the post? Please let us know using our contact page and we will update it with due credits!
If you wish to contribute radiological images for this case (or any other article on the website), you can submit them here and you will be duly credited: Submit radiology case