

This calculator implements ACR/ESUR PI-RADS 2.1 rules. Decisions should be clinical, not solely based on this tool.
| 1 | Very low | ~2% | Sig. cancer is highly unlikely |
| 2 | Low | ~4% | Sig. cancer is unlikely |
| 3 | Intermediate | ~20% | Equivocal |
| 4 | High | ~52% | Likely present |
| 5 | Very high | ~89% | Highly likely |
DWI=3: Requires DCE assessment
DWI=4 or 5: PI-RADS 4, 5 (immediate result)
T2W=2,3: Requires DWI assessment
T2W=4,5: PI-RADS 4,5 (immediate result)
Key facts for practice and radiology board exams
PI-RADS v2.1 grades prostate MRI from 1 to 5 for the likelihood of clinically significant cancer. Pooled patient-level detection rates are about 3% at PI-RADS 1, 6% at 2, 20% at 3, 53% at 4 and 83% at 5. [1] Diffusion-weighted imaging decides the score in the peripheral zone; T2-weighted imaging decides it in the transition zone. [2]
- v2.1 is still the current version. There is no PI-RADS 3.0, and the Steering Committee has said a major version change is not yet appropriate. [3]
- The zone sets the dominant sequence. Scoring a transition zone nodule by its ADC map is the commonest beginner error.
- DCE does one job. It upgrades a peripheral zone 3 to a 4 when enhancement is focal and early. It never rescues a 1, 2, 4 or 5. [2][3]
- PI-RADS 3 is the problem category, and PSA density is the usual tie-breaker, at a cost. [4]
- Agreement is only substantial, and v2.1 did not measurably improve it over v2.0. [5]
What each PI-RADS score actually means
The assessment category is a probability statement, not a diagnosis. The figures below are patient-level pooled rates for clinically significant cancer from a 2026 meta-analysis of 117 studies, 25,228 patients and 15,553 lesions. [1]
PI-RADS Likelihood of clinically significant cancer Pooled detection rate [1] Usual consequence 1 Highly unlikely About 3% No targeted biopsy 2 Unlikely About 6% No targeted biopsy 3 Equivocal About 20% Decision depends on PSA density and clinical risk 4 Likely About 53% Targeted biopsy 5 Highly likely About 83% Targeted biopsy, assess local staging
Threshold performance follows from the same pooled data. Reporting PI-RADS 3 or above as positive gives a sensitivity of 96% with a specificity of 43%. Moving the threshold to 4 or above drops sensitivity to 88% but lifts specificity to 66%. [1] That trade is the whole argument about what to do with a 3.
Peripheral zone: diffusion decides
In the peripheral zone the DWI and ADC score becomes the PI-RADS category directly, with one exception. A DWI score of 3 is referred to dynamic contrast enhancement: positive focal early enhancement that matches the suspicious finding makes it a PI-RADS 4, and a negative study leaves it at 3. [2][3]
DWI score Finding on ADC and high b-value DWI PI-RADS 1 Normal 1 2 Linear or wedge-shaped signal change 2 3 Focal, markedly abnormal on ADC or high b-value, not both 3, or 4 if DCE positive 4 Focal, markedly abnormal on both, under 1.5 cm 4 5 As score 4 but 1.5 cm or larger, or extraprostatic extension 5
Transition zone: T2 decides, diffusion can upgrade
The transition zone is full of benign hyperplastic nodules, so T2-weighted morphology leads and DWI is the modifier. v2.1 formalised two upgrade rules that v2 left vague. An atypical nodule scoring T2 2 becomes PI-RADS 3 when DWI is 4 or more, the so-called 2 plus 1 rule. A T2 3 lesion becomes PI-RADS 4 when DWI is 5. [2][3]
These rules were validated in a meta-analysis of 8 studies and 1,535 transition zone lesions, and the headline is that they sort lesions into the right band rather than inflating scores. Upgraded 2 plus 1 lesions yielded clinically significant cancer in 13% (95% CI 6 to 23), statistically indistinguishable from a native PI-RADS 3 at 19% (odds ratio 0.80, 95% CI 0.44 to 1.45). Upgraded T2 3 lesions yielded 37% (95% CI 24 to 52), close to a native PI-RADS 4 at 49%. [6]
T2 score DWI score Final PI-RADS Clinically significant cancer [6] 2 Under 4 2 6% 2 4 or 5 3 (2 plus 1 rule) 13% (6 to 23) 3 Under 5 3 19% 3 5 4 37% (24 to 52) 4 Any 4 49%
One prospective series disagrees for the 2 plus 1 group, finding clinically significant cancer in 4% of upgraded nodules against 20% of non-upgraded ones. [7] It rests on a single cancer in 26 upgraded lesions, and two other series found lower but non-significant differences, so the meta-analysis remains the better guide. Do not report an upgraded nodule as low risk.
Is there a PI-RADS version 3?
No. v2.1, published in 2019, is still current. [2] The PI-RADS Steering Committee has set an explicit evidence bar for changing versions: a minor update such as a v2.2 needs at least one adequately powered single-centre cohort study, and a full version upgrade to PI-RADS 3.0 needs at least one multicentre cohort study showing significant clinical benefit. That bar has not been met, and the Committee concluded a major version transition is not yet appropriate. [3]
What is coming instead is a PI-RADS pathway position statement, a risk-based framework that combines the MRI category with PSA density and clinical history to drive the biopsy decision, rather than a renumbering of the scale. [3] Reports written to v2.1 today will not need rescoring.
PI-RADS 3, PSA density and the honest numbers
About one in five PI-RADS 3 lesions harbours clinically significant cancer, [1] which is precisely the range in which neither biopsying everyone nor biopsying no one is defensible. PSA density is the usual tie-breaker, and the commonly quoted cut-off of 0.15 ng/mL/mL is an optimal value from retrospective cohorts rather than a validated threshold.
- Omitting biopsy below a PSA density of 0.15 spared 71.5% of men a biopsy but missed 15.0% of clinically significant cancers in one single-centre series of 158 patients. [4]
- Sensitivity at that cut-off was 0.51 and specificity 0.78, so it is a triage tool, not a rule-out test. [4]
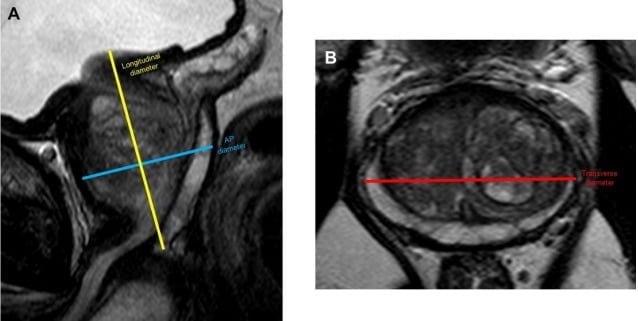
- Report gland volume with the three diameters so the referrer can compute density: transverse by longitudinal by anteroposterior by 0.52. [2]
- State the zone, the dominant sequence finding and whether DCE was used, because an equivocal score means different things in each zone.
Acquisition settings that change the score
v2.1 tightened the technical minimum, because an under-specified sequence changes the category rather than merely degrading the picture. A high b-value image reconstructed from inadequate source data is the usual reason a genuine 4 is read as a 3.
| Parameter | PI-RADS v2.1 requirement [3] |
|---|---|
| Low b-value | 50 to 100 s/mm2 |
| Intermediate b-value | 800 to 1000 s/mm2, used with the low value to calculate ADC |
| High b-value | At least 1400 s/mm2, acquired separately or calculated |
| ADC map | Computed only from b-values of 1000 or less |
| DCE temporal resolution | 15 seconds or less, tightened from 10 seconds in v2 |
Whether dynamic contrast can be dropped altogether is unsettled. A 2026 meta-analysis of 40 studies and 9,403 patients found biparametric MRI non-inferior to multiparametric at the patient level, with a sensitivity difference of 2.3 percentage points. [8] A second 2026 meta-analysis of 25 studies found multiparametric sensitivity significantly higher. [9] v2.1 itself gives no recommendation on when the shorter protocol may replace the full one. [3]
How reproducible is a PI-RADS score?
Pooled inter-reader agreement for v2.1 across 12 studies and 2,475 patients is a kappa of 0.65 (95% CI 0.56 to 0.73) for the whole gland, falling to 0.62 in the transition zone. Reader experience of five years or more was the one factor that significantly improved it. Head to head, v2.1 did not beat v2.0 to a significant degree, at 0.64 against 0.57. [5] The version tightened the definitions; it did not make readers agree.
Frequently asked questions
What is a PI-RADS score?
Does PI-RADS 3 mean cancer?
Is there a PI-RADS version 3?
What is the 2 plus 1 rule in PI-RADS v2.1?
What PSA density threshold is used for a PI-RADS 3 lesion?
References
- Nedelcu A, Oerther B, Benkendorff A, Dieckbreder S, Schwarzer G, Agrotis G, et al. PI-RADS Version 2.1 for Prostate MRI Interpretation: Associations of Study Quality and Cancer Detection Metrics-A Systematic Review and Meta-Analysis. AJR Am J Roentgenol. 2026;226(2):e2533583. PMID: 41090646.
- Turkbey B, Rosenkrantz AB, Haider MA, Padhani AR, Villeirs G, Macura KJ, et al. Prostate Imaging Reporting and Data System Version 2.1: 2019 Update of Prostate Imaging Reporting and Data System Version 2. Eur Urol. 2019;76(3):340-351. PMID: 30898406.
- Ponsiglione A, Schoots IG, Padhani AR. The evolving PI-RADS paradigm. Cancer Imaging. 2026;26(1):86. PMID: 42152154.
- Nguyen TA, Fourcade A, Zambon A, Saout K, Deruelle C, Joulin V, et al. Optimal PSA density threshold and predictive factors for the detection of clinically significant prostate cancer in patient with a PI-RADS 3 lesion on MRI. Urol Oncol. 2023;41(8):354.e11-354.e18. PMID: 37391283.
- Wen J, Ji Y, Han J, Shen X, Qiu Y. Inter-reader agreement of the prostate imaging reporting and data system version v2.1 for detection of prostate cancer: A systematic review and meta-analysis. Front Oncol. 2022;12:1013941. PMID: 36248983.
- Agrotis G, Pooch EP, Marsitopoulos K, Vlychou M, Benndorf M, Beets-Tan RGH, et al. Detection rates for prostate cancer using PI-RADS 2.1 upgrading rules in transition zone lesions align with risk assessment categories: a systematic review and meta-analysis. Eur Radiol. 2025;35(10):6454-6465. PMID: 40287872.
- Yilmaz EC, Shih JH, Belue MJ, Harmon SA, Phelps TE, Garcia C, et al. Prospective Evaluation of PI-RADS Version 2.1 for Prostate Cancer Detection and Investigation of Multiparametric MRI-derived Markers. Radiology. 2023;307(4):e221309. PMID: 37129493.
- Strieder de Oliveira G, Altmayer S, Torri GB, Prediger JE, Abreu-Gomez J, Ghai S, et al. Diagnostic Performance of Biparametric versus Multiparametric Magnetic Resonance Imaging for Prostate Cancer Diagnosis: An Updated Systematic Review and Meta-analysis. Eur Urol. 2026;90(1):19-31. PMID: 41702800.
- Zhu G, Xiong X, Xu H, Zheng W, Wang S, Yang J, et al. Abbreviated biparametric versus multiparametric MRI for the detection of clinically significant prostate cancer in treatment-naive patients: a diagnostic test accuracy systematic review and meta-analysis. Int J Surg. 2026;112(2):5049-5060. PMID: 41231653.
Improve Content And Help Your Colleagues!
Found an error in the post? Please let us know using our contact page and we will update it with due credits!
If you wish to contribute radiological images for this case (or any other article on the website), you can submit them here and you will be duly credited: Submit radiology case
About the Author
Dr. Amar Udare, MD, DNB
Dr. Udare holds an MBBS and MD degree, and his expertise lies in the field of radiology. He has authored multiple peer-reviewed publications, contributing significantly to the medical field. His works can be accessed on PubMed and Google Scholar.
In addition to his academic and professional achievements, Dr. Udare is an avid reader and enjoys exploring the latest advancements in medical technology. His commitment to making complex medical knowledge accessible to patients and the general public aligns with our mission at RadioGyan.com.
For any further questions or clarifications, feel free to reach out to Dr. Udare via the contact form.