


Key facts for practice and radiology board exams
Edwards syndrome is trisomy 18, the second commonest autosomal trisomy, about 1 in 6,000 to 8,000 live births [1]. On the anomaly scan look for a growth restricted fetus with clenched overlapping fingers, rocker-bottom feet, a strawberry-shaped skull and a ventricular septal defect with thickened dysplastic valves. One year survival is about 13%, not the under 10% usually quoted [2].
Clinical features of Edwards syndrome
The phenotype is a combination, not any single finding. No feature below is specific on its own, but three or four together in a small-for-dates fetus make trisomy 18 the leading diagnosis.
| System | Features |
|---|---|
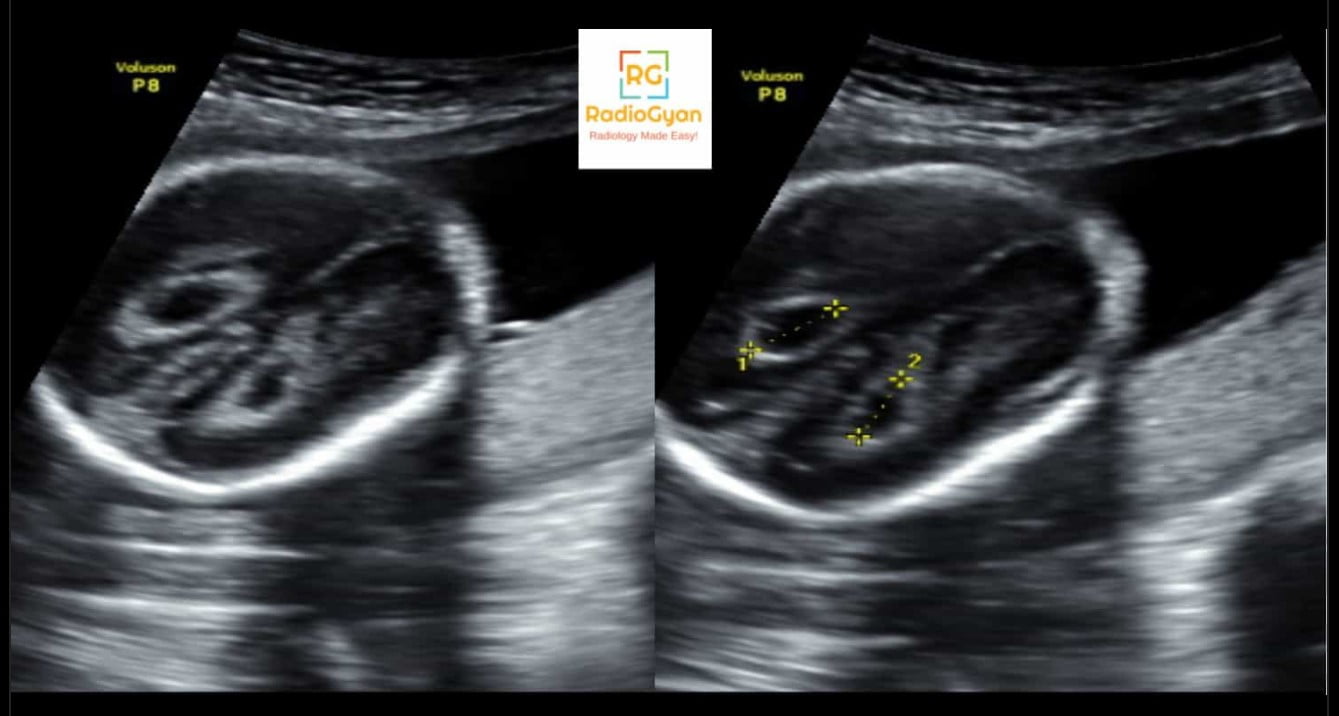
| Craniofacial | Microcephaly, strawberry-shaped skull (flattening of the occiput with pointing of the frontal bones [6]), micrognathia, short palpebral fissures, small mouth, low-set malformed ears |
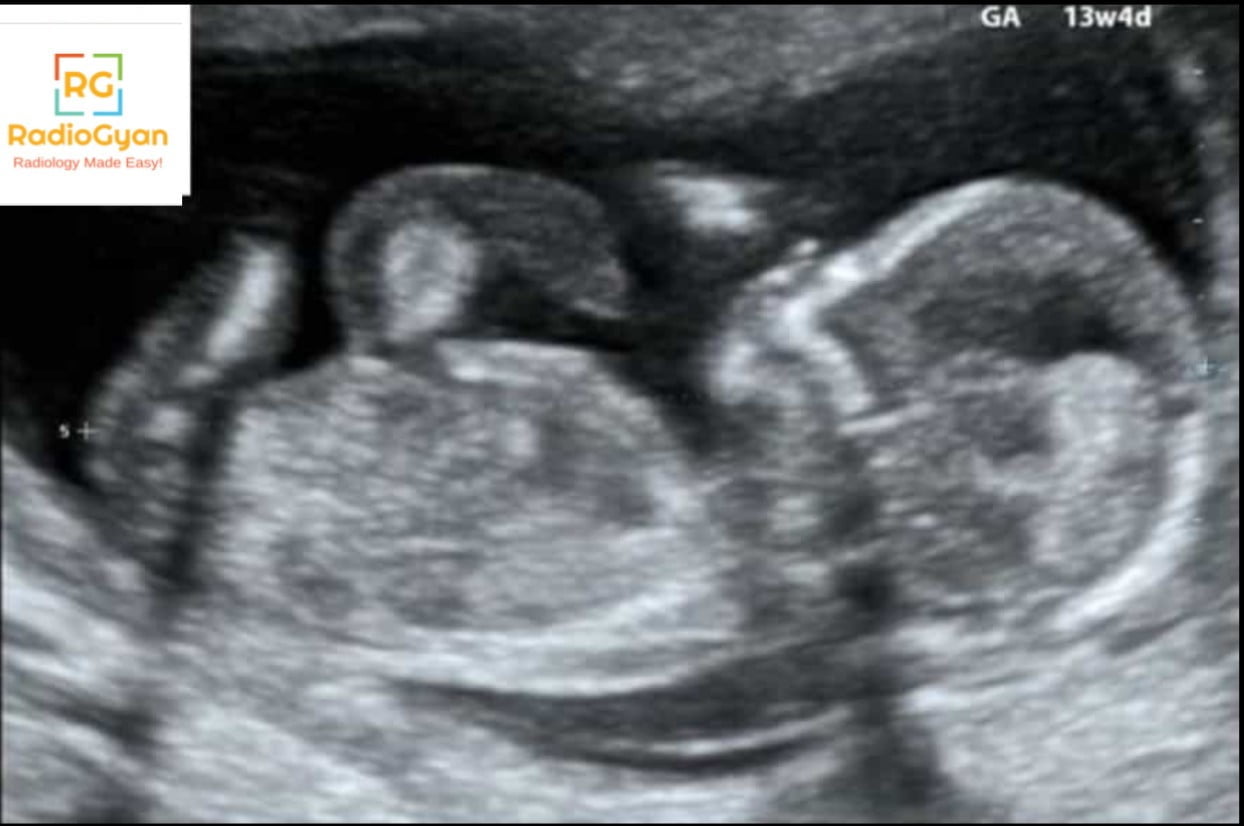
| Hands and feet | Clenched hand with the index finger overlapping the third digit and the fifth overlapping the fourth, hypoplastic nails, radial ray defects, rocker-bottom feet with a prominent calcaneus |
| Cardiac | Ventricular septal defect, and polyvalvular disease (thickened redundant myxomatous leaflets of two or more valves), which is the near-specific lesion [4] |
| Central nervous system | Choroid plexus cysts, mild ventriculomegaly, agenesis of the corpus callosum, posterior fossa anomalies, meningomyelocele |
| Abdomen and renal tract | Omphalocele, diaphragmatic hernia, oesophageal atresia, horseshoe kidney, hydronephrosis |
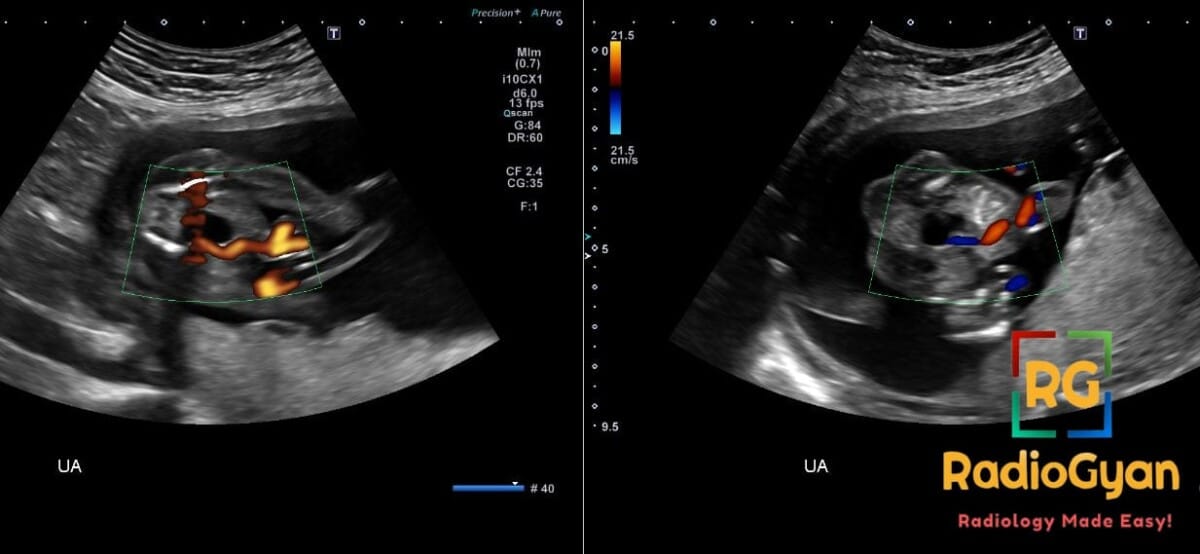
| Pregnancy | Early fetal growth restriction, polyhydramnios, a small placenta, single umbilical artery |
Prenatal ultrasound findings in trisomy 18
Trisomy 18 is one of the more reliably detected aneuploidies because the findings are multiple and structural rather than isolated soft markers. In a prospective series of 5,650 first trimester scans, only 1 of 37 affected fetuses (2.7%) had no marker of aneuploidy at 11 to 13 weeks, extracardiac malformations were present in 35.1% and a congenital heart defect in 70.3% [5]. Mean nuchal translucency was 5.4 mm against 1.7 mm in euploid fetuses. The five first trimester findings worth a deliberate search are increased nuchal translucency, tricuspid regurgitation, a single umbilical artery, omphalocele and a right dominant heart [5].

At the mid-trimester scan, performed to the ISUOG protocol [11], the most useful observation is a behavioural one: the fetal hand stays clenched with the fingers overlapping and never opens through the study. A hand that opens at any point is normal. Add rocker-bottom feet, the skull shape, a cardiac defect and growth restriction with polyhydramnios and the picture is close to diagnostic.
Cardiac defects in trisomy 18
A cardiac defect is close to universal, but the useful finding is which one. In 41 autopsied hearts, every case had a ventricular septal defect and 38 of 41 (93%) had polyvalvular disease, with thickened redundant myxomatous leaflets affecting two or more valves [4]. That series is autopsy-selected, so treat the 100% as an upper bound: the prospective first trimester figure is 70.3% [5]. A septal defect on its own is common and non-specific. Polyvalvular disease is what should move trisomy 18 up the list.
Screening and diagnosis: where cell-free DNA fits
Cell-free DNA is a screening test, not a diagnosis. Pooled detection for trisomy 18 is 97.9% with a false positive rate of 0.04% [7]. The number that matters in counselling is the positive predictive value, which is lower than for trisomy 21 and depends heavily on prior risk. In a prospective cohort with genetic confirmation it was 50.0% in low risk and 81.3% in high risk women, against 85.7% and 97.5% for trisomy 21 [8]. ACOG and SMFM recommend offering both screening and diagnostic testing to all patients, whatever their age [9].
- A positive screen is confirmed by chorionic villus sampling or amniocentesis before any irreversible decision.
- An isolated choroid plexus cyst with a negative serum or cell-free DNA screen needs no further aneuploidy evaluation. With no prior screening, offer cell-free DNA or a quad screen rather than diagnostic testing [10].
- An isolated single umbilical artery is handled the same way: no additional aneuploidy evaluation [10].
- Fetal MRI adds little for the diagnosis itself. Reserve it for corpus callosum or posterior fossa questions the ultrasound cannot settle.
Differential diagnosis
| Condition | What separates it from trisomy 18 |
|---|---|
| Trisomy 13 (Patau syndrome) | Midline defects dominate: holoprosencephaly, cleft lip and palate, hypotelorism. Postaxial polydactyly rather than overlapping fingers |
| Trisomy 21 (Down syndrome) | Soft markers rather than major structural anomalies. Atrioventricular septal defect, duodenal atresia, nuchal thickening. Growth is usually preserved |
| Triploidy | Severe asymmetric early growth restriction with relative head sparing, and often an enlarged cystic placenta rather than the small placenta of trisomy 18 |
| Meckel-Gruber syndrome | The triad of occipital encephalocele, enlarged cystic dysplastic kidneys and postaxial polydactyly. Oligohydramnios, not polyhydramnios |
Genetics, recurrence risk and prognosis
The extra copy of chromosome 18 produces a gene dosage imbalance that disturbs organogenesis broadly, which is why the malformations span the heart, brain, limbs and abdominal wall rather than following one developmental field. Cytogenetic subtype, however, is what drives outcome.
- Survival tracks the karyotype. In a Texas registry, 10 year survival was 6.6% for full trisomy 18 against 43.8% for mosaic or partial trisomy 18 (hazard ratio for full trisomy 3.34, 95% CI 2.08 to 5.38) [3].
- In an Ontario population cohort, median survival after live birth was 9 days (IQR 2 to 92) and 1 year survival was 12.6% (95% CI 8.9 to 17.1) [2].
- Recurrence risk after a child with full trisomy 18 is about 1% [1].
- The incompatible with life framing is being reassessed [3]. In the same Ontario cohort 13.8% of children underwent surgery and 1 year survival after a first surgery was 68.6% (95% CI 50.5 to 81.2) [2]. That is a selected group with no matched comparison, so it is not evidence that surgery causes the difference. It does mean prognosis is now individualised rather than assumed.
Related cases on RadioGyan
- Bilateral choroid plexus cysts
- Omphalocele
- Increased nuchal translucency
- Single umbilical artery
- Spotters set 20: fetal ultrasound
Frequently asked questions
References
- Cereda A, Carey JC. The trisomy 18 syndrome. Orphanet J Rare Dis. 2012;7:81. PMID: 23088440.
- Nelson KE, Rosella LC, Mahant S, Guttmann A. Survival and surgical interventions for children with trisomy 13 and 18. JAMA. 2016;316(4):420-428. PMID: 27458947.
- Ludorf KL, Benjamin RH, Shumate CJ, Canfield MA, Nguyen J, Agopian AJ. Long-term survival among children with trisomy 13 and trisomy 18 by cytogenetic status. JAMA Netw Open. 2025;8(9):e2529885. PMID: 40920381.
- Van Praagh S, Truman T, Firpo A, Bano-Rodrigo A, Fried R, McManus B, et al. Cardiac malformations in trisomy-18: a study of 41 postmortem cases. J Am Coll Cardiol. 1989;13(7):1586-1597. PMID: 2723271.
- Wiechec M, Knafel A, Nocun A, Matyszkiewicz A, Wiercinska E, Latala E. How effective is ultrasound-based screening for trisomy 18 without the addition of biochemistry at the time of late first trimester? J Perinat Med. 2016;44(2):149-159. PMID: 25803072.
- Nicolaides KH, Salvesen DR, Snijders RJ, Gosden CM. Strawberry-shaped skull in fetal trisomy 18. Fetal Diagn Ther. 1992;7(2):132-137. PMID: 1503648.
- Gil MM, Accurti V, Santacruz B, Plana MN, Nicolaides KH. Analysis of cell-free DNA in maternal blood in screening for aneuploidies: updated meta-analysis. Ultrasound Obstet Gynecol. 2017;50(3):302-314. PMID: 28397325.
- Dar P, Jacobsson B, MacPherson C, Egbert M, Malone F, Wapner RJ, et al. Cell-free DNA screening for trisomies 21, 18, and 13 in pregnancies at low and high risk for aneuploidy with genetic confirmation. Am J Obstet Gynecol. 2022;227(2):259.e1-259.e14. PMID: 35085538.
- American College of Obstetricians and Gynecologists’ Committee on Practice Bulletins-Obstetrics, Committee on Genetics, Society for Maternal-Fetal Medicine. Screening for fetal chromosomal abnormalities: ACOG Practice Bulletin, number 226. Obstet Gynecol. 2020;136(4):e48-e69. PMID: 32804883.
- Prabhu M, Kuller JA, Biggio JR; Society for Maternal-Fetal Medicine. Society for Maternal-Fetal Medicine Consult Series #57: evaluation and management of isolated soft ultrasound markers for aneuploidy in the second trimester. Am J Obstet Gynecol. 2021;225(4):B2-B15. PMID: 34171388.
- Salomon LJ, Alfirevic Z, Berghella V, Bilardo CM, Chalouhi GE, Da Silva Costa F, et al. ISUOG Practice Guidelines (updated): performance of the routine mid-trimester fetal ultrasound scan. Ultrasound Obstet Gynecol. 2022;59(6):840-856. PMID: 35592929.

Improve Content And Help Your Colleagues!
Found an error in the post? Please let us know using our contact page and we will update it with due credits!
If you wish to contribute radiological images for this case (or any other article on the website), you can submit them here and you will be duly credited: Submit radiology case